
Dr Sharmistha

IVF Treatment

Life During and After IVF Treatment: What Patients Should Know

Beginning the IVF (In Vitro Fertilization) process is one of the most important choices couples can take in their adventure towards parenthood. While the most focus goes to the medical process itself, in reality, the patients may want to understand what happens during their everyday life in the course of treatment and also after it is over. Knowing what each phase involves can be very beneficial in terms of alleviating anxiety around the process. Understanding the IVF Journey: An Overview IVF is a multi-step process that typically spans four to six weeks per cycle. It involves ovarian stimulation, egg retrieval, fertilization in a laboratory, and embryo transfer. While the science behind IVF has advanced tremendously, every patient’s experience is unique, shaped by their medical history, age, and underlying fertility challenges.   Many patients searching for guidance turn to a trusted infertility specialist in Siliguri to better understand their treatment options and what lies ahead. Having the right medical support during this time makes a meaningful difference-not just in success rates, but in how manageable the entire experience feels. Life During IVF Treatment 1. The Stimulation Phase The process normally starts with hormone injections aimed at stimulating the ovary to release many eggs. This phase lasts for 8-14 days, during which the patient is supposed to:   Have frequent visits to the clinic to undergo blood and ultrasound tests for follicles’ measurement Experience bloating, sore breasts, or mood changes resulting from the effects of hormones Need to inject regularly in a timely manner It is crucial to communicate openly with your fertility doctors during this stage. Any symptoms, such as severe stomach pain or weight gain, should be reported immediately since they may indicate Ovarian Hyperstimulation Syndrome (OHSS). 2. Egg Retrieval and Fertilization After the eggs have attained the right size, a small surgery is conducted to collect the eggs, which only takes one or two days for the patient to recover, although there may be some cramping and light bleeding. The collected eggs are then combined with sperm in the lab through insemination or ICSI. 3. Embryo Transfer and the Two-Week Wait Three to five days after the development of the embryo, the embryos are implanted in the uterus. The following process is referred to as the infamous “two-week wait,” which is the waiting period from implantation to the pregnancy test. This period is known as the most difficult emotional stage of IVF.   Some tips for this period are: Do not engage in strenuous exercises but keep your routine activities light Take the prescribed progesterone medications regularly Use stress management strategies such as walking or meditation Do not look out for signs, since symptoms of pregnancy and side effects of medicines are alike Managing the Emotional Rollercoaster IVF is a process which can prove quite emotional. Patients tend to feel a variety of emotions such as fear, hope, disappointment, among others and all on one single day. This is very normal.   Some ways of coping include:   Creating a network of supporters. You can talk to a partner, friend or a support group which will make you feel less alone. Try counseling. More often than not, many clinics will have counselors in place for their patients to help cope with fertility related stress. Set boundaries with those people who do not seem to appreciate the emotional toll that comes with the process. Be patient with your body. Hormones will play a big role in affecting your moods and energy level. What Happens After a Positive Pregnancy Test? A positive beta hCG result means that it’s time for happiness and peace of mind, but there is much more ahead. Some steps still need to be taken during the first trimester after conception through IVF procedure:   Continuing hormonal therapy: Estrogen and progesterone therapies continue until week 8-12 of the pregnancy period. Early ultrasound scans: They detect pregnancy position (check for ectopic pregnancy) and detect the fetal heart rate at week 6-7 of pregnancy. Regular monitoring: An IVF pregnancy requires slightly more regular examinations due to the presence of preconditions like PCOS or an advanced age of patients. Once the pregnancy becomes stable and is passed from the first trimester stage, a normal OB/GYN schedule can be followed. What If the Cycle Is Unsuccessful? Not every in vitro fertilization cycle leads to pregnancy, and that is one of the most difficult facts patients have to cope with. When a cycle does not work, it should be remembered that:   One failure does not automatically mean future failures Your fertility doctor usually analyzes the cycle thoroughly and makes adjustments necessary Having more frozen embryos will give you an opportunity to conduct another cycle without conducting the whole stimulation again It is completely natural to take some time to mourn and recover before making the next step Communicating openly with your doctors about what did not work well and what should be adjusted is one of the key points of the process. Long-Term Physical Health After IVF In addition to the immediate consequences, women have concerns over what IVF means for their health in the future. According to recent scientific studies, IVF does not harm a person and causes only temporary physical consequences linked to hormonal therapy. But keeping up a healthy lifestyle – eating properly, exercising moderately, and avoiding stress – helps you stay in good reproductive and general condition, regardless of the treatment result.   It is important to have regular check-ups even when the treatment has been successful or unsuccessful. Practical Tips for Patients Undergoing IVF Maintain a treatment calendar: Log in medications, appointments, and test results to keep track. Schedule recovery periods: This is particularly important around the time of retrieval and transfer. Consult with work if necessary: Some patients choose to discuss their situation with the employer for scheduling, and others prefer not to-it depends on your personal choice. Do not hesitate to ask questions: Any and all questions are relevant in the case of your

Life During and After IVF Treatment: What Patients Should Know Read More »

Can Endometriosis Cause Infertility? Understanding the Connection

Being diagnosed with endometriosis, or perhaps even suspecting that you may have it, will bring up a number of questions in your mind, but one in particular that will definitely be prominent is whether endometriosis causes infertility. This is a legitimate worry, as there are quite a few cases where women are facing this issue and don’t get the right information or help from anyone. But the thing is that endometriosis-induced infertility is not something unknown in medical circles, and, if you consult an expert fertility doctor, you will be able to become pregnant successfully.. What is Endometriosis? Endometriosis is an illness wherein tissues like that lining the uterus are found outside the uterus – most likely growing on the ovaries, fallopian tubes, and the lining tissues of the pelvis. But unlike the uterine lining tissue that sheds itself during the menstrual period, this tissue has nowhere to go once it is shed. Hence, it causes inflammation, scarring, and adhesions (scar tissues that make the organs bind to each other).   There are millions of sufferers of endometriosis all around the world, but many of them remain undiagnosed for several years as the symptoms are usually dismissed as just menstrual pains. Common Symptoms of Endometriosis Periods (dysmenorrhea) that cause severe pain that increases with time Sexual pain Pelvic pain that is not limited to periods Severe period bleeding or bleeding outside of periods Digestion problems like bloating, constipation, or diarrhea, particularly during your periods Fatigue Difficulty becoming pregnant These are some of the signs and symptoms that indicate you may need to see an infertility specialist. So, Can Endometriosis Cause Infertility? Absolutely, because endometriosis is one of the main reasons for women’s infertility. The researches show that there is a certain percentage of women who have trouble with conception, ranging from 30 to 50%. But it should be taken into account that not all women suffering from endometriosis will face the problem of infertility, because it does not necessarily depend on the severity of endometriosis. Let’s see how endometriosis can prevent conception. 1. Distorted Pelvic Anatomy With the growth of endometrium-like tissue and formation of scar tissue, the ovaries, fallopian tubes, and uterus may get displaced. This displacement of organs will make it hard for the egg cell to move from the ovary to the fallopian tube, thus preventing fertilization. 2. Blocked or Damaged Fallopian Tubes In the most severe case, endometriosis will lead to the development of adhesions which will block the fallopian tubes completely, thus preventing the sperm cell from getting to the egg or vice versa. 3. Inflammation Affecting Egg and Sperm Quality Endometriosis can cause chronic inflammation in the pelvic cavity. This inflammation might affect not only the egg and sperm cells but also the embryo itself. 4. Ovarian Reserve Reduction Chocolate cysts, which are also known as endometriomas, are one form of ovarian cysts related to endometriosis. Endometrioma can destroy normal ovarian tissue and decrease the woman’s ovarian reserve, meaning the amount of good quality eggs that can be used in conception. 5. Implantation Issues Although fertilization might happen, endometriosis can make the uterus not receptive enough for the implantation of the embryo. Diagnosing Endometriosis-Related Infertility In case you have been struggling with conception problems and think that you may have endometriosis, meeting an expert in infertility would be your initial move. The diagnostic procedure usually includes:   Detailed medical history and symptom review Pelvic examination Ultrasound imaging to detect cysts or abnormalities Laparoscopy, considered the gold standard for confirming endometriosis, which allows direct visualization and, in many cases, treatment during the same procedure Dr. Sharmistha Sarkar emphasizes the importance of early diagnosis, as timely intervention can significantly improve fertility outcomes for women with endometriosis. Treatment Options for Endometriosis and Infertility The correct treatment depends on the severity of the disorder, the woman’s age, and the duration of her efforts to get pregnant. The following treatment modalities are commonly used: Medication Treatment It helps to control pain and to slow down the progression of endometriosis; however, hormonal therapy is usually avoided while a woman is trying to conceive because most medications affect the ovulation process. Laparoscopy This minimally invasive procedure allows for the removal of endometrial tissue, cysts, and adhesions and increases fertility, especially if endometriosis is mild to moderate. Ovulation Induction Fertility drugs and controlled ovulation may assist in getting pregnant naturally in the case of mild endometriosis. Intrauterine Insemination (IUI) In some cases, intrauterine insemination is indicated along with ovulation induction. In Vitro Fertilization (IVF) If a woman has endometriosis to the extent that she has problems conceiving by other methods, In Vitro Fertilization (IVF) will be the most appropriate method for her. In vitro fertilization will avoid many of the issues that the condition causes in conception.   An experienced fertility specialist will design a personalized treatment program for each woman. Living with Endometriosis While Trying to Conceive However, having endometriosis does not automatically exclude a woman from pregnancy. There are many cases where women with this disease have successfully conceived both naturally and artificially. Here are some pieces of advice that might come in handy when attempting to conceive with endometriosis:   Do not waste time. Seek professional help immediately if you cannot conceive for six months to a year (or even before, if you are older than 35 years). Monitor your symptoms. Your doctor will need to know your experience of pain and the menstrual cycle in order to make the right diagnosis. Try every possible treatment. Whether it is lifestyle adjustment or complex assisted reproductive technologies, there are numerous ways to get pregnant. Look for psychological support. Dealing with fertility problems may be psychologically stressful, and discussing your issues with people who can listen is very important. Why Choose Dr. Sharmistha Sarkar Tackling infertility associated with endometriosis demands a sensitive, experienced, and meticulous method. Being an infertility specialist with extensive experience in dealing with women experiencing fertility problems, Dr. Sharmistha Sarkar is well equipped to provide personalized treatment

Can Endometriosis Cause Infertility? Understanding the Connection Read More »

Blocked Fallopian Tubes: Causes, Symptoms, and Treatment

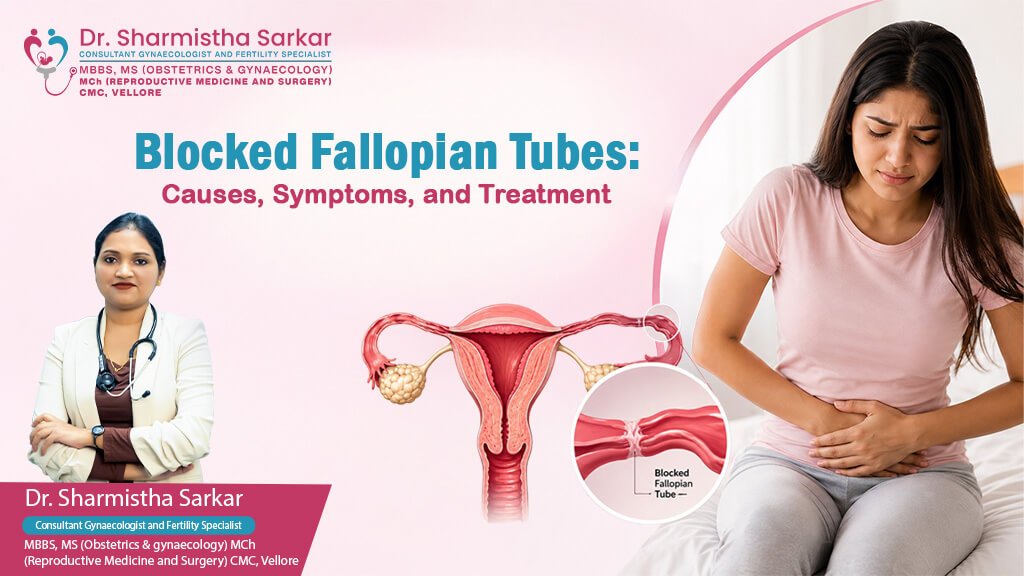
If you’ve been attempting to conceive without any success, you might have to seek out help. You’re not alone. No one knows why, and many women suffer from this silently. Hope is constantly replaced by frustration, every month. Test results are normal, but the pregnancy does not occur. Frequently, blocked fallopian tubes are overlooked.   There are relatively few symptoms of this condition. However, it is a significant factor in fertility problems in the world.   It is believed to be one of the main contributors to 20% of the cases of unexplained infertility in clinics today.   Let’s take this apart. Simply. Clearly. Without the jargon used by doctors. What Are Fallopian Tubes and How Do They Work? Consider these like miniature highways. Fallopian Tubes are tubes that link your ovary to your uterus.   This tube is used to transport an egg each month. Sperm and egg form a zygote, or fertilized egg, here. Now, just suppose that the highway is blocked.   The egg is unable to move. Sperm will not be able to make it there. As long as they cannot get them to breed.   So what is a tubal blockage? And it is more prevalent than most women think.   The blockage could occur anywhere on the tube. Near the ovary. In the middle. Or just at the point where it is attached to the uterus. The place is important as it will influence diagnosis and treatment options later. Why Fallopian Tube Health Matters for Fertility There are numerous factors that influence fertility.   Hormones. Ovulation. Uterine health. And importantly, open, functional tubes. If there’s a blockage in the fallopian tube, even if the hormones are perfect, pregnancy may be impossible.   That’s why doctors always examine tube health when evaluating fertility. It’s a part of a puzzle that’s simple to overlook, but hard to overlook.   A large proportion of the female infertility cases that are encountered in the clinics today are due to blocked fallopian tubes. Common Symptoms of Fallopian Tubes Here’s the tricky part. Most women do not experience anything abnormal.   That’s right. Blocked fallopian tube symptoms can be vague, sometimes not present at all, which is why women may not find out they have a blocked fallopian tube until they are undergoing fertility testing.   However, some symptoms might occur such as: Slight to medium pain in the pelvis area. Unusual vaginal discharge Periods that are painful, worse than usual Pain during intercourse The doctor will ask you about any previous infections you’ve had in the pelvis. If you see these signs and complain of trouble getting pregnant, it’s advisable to get checked. Prevention is better than cure.   Take care – no symptoms, no problems! That’s why fertility testing is important – it can detect what the average person can’t. What Causes for Blocked Fallopian Tubes? The knowledge of the cause assists in providing appropriate treatment.   These are the most usual causes of blocked Fallopian tubes:   Pelvic Inflammatory Disease (PID) – May be due to untreated sexually transmitted infections such as chlamydia or gonorrhea. This is one of the main causes of damage to the tubes.   Endometriosis – Growth outside of the womb may be able to entangle or scar the tubes.   Previous surgeries – Surgery to the abdomen or pelvis may cause scar tissue to develop and obstruct the tubes.   Ectopic pregnancy history – Scars and damage to the affected tube can occur after an ectopic pregnancy.   Fibroids – If there is a large fibroid near the tubes, sometimes it can put pressure on the tubes and block them.   Untreated infections – If left untreated for too long, the risk of an infection of the pelvis is greatly increased.   Tuberculosis – Genital tuberculosis is an unrecognized but actual cause of tubal scarring in some areas.   If your doctor knows your past history, he or she can quickly identify the likely cause. How Are Blocked Fallopian Tubes Diagnosed? There are a few key tests that are typically used to diagnose.   Hysterosalpingography (HSG) – A special dye is inserted into the cervix. After this, X-rays will be taken to determine if the dye can flow freely through the tubes. This procedure is still the most frequently used to diagnose fallopian tube blockage.   Laparoscopy – A minor surgical procedure using a small camera. This enables them to see blockages and other pelvic problems directly.   Sonohysterography – A test that uses ultrasound, which is sometimes used as the first screening test.   None of these tests are intended to frighten you. They just provide your doctor with a map of what’s going on inside, and guesswork is replaced by facts. The correct test will be suggested according to your medical history and symptoms. Blocked Fallopian Tubes and Infertility: What’s the Connection? Let’s address this directly.   Blocked tubes and infertility are closely linked, but a blockage doesn’t always mean pregnancy is impossible.   If only one tube is blocked, natural conception may still happen through the healthy tube.   If both tubes are blocked, natural conception becomes very difficult. But medical treatments still offer real hope.   This is why proper diagnosis matters so much. It tells you exactly what you’re working with, not just guessing based on symptoms alone. Blocked Fallopian Tubes Treatment: Options That Work Next, the part you’ve all been waiting for.   If you have blocked fallopian tubes treatment will vary depending on the location and severity of the blockage.   Tubal surgery – Sometimes, surgeons will be able to remove scar tissue and open the tube. The extent of the damage is the determining factor for success.   Laparoscopic surgery – A simple procedure that may be used for mild blockages or to remove scar tissue.   In Vitro Fertilisation (IVF) – IVF is used when tubes are so damaged or surgery unsuccessful. The egg and sperm fuse in the ‘outside’, and the

Blocked Fallopian Tubes: Causes, Symptoms, and Treatment Read More »

The Real Truth About Infertility: A Letter From Dr. Sharmistha Sarkar

If you’re reading this right now, there’s a good chance you’re doing it alone. Or maybe your partner is sitting beside you, but you both feel miles apart. Maybe you’re at work, pretending everything is fine, while inside you’re breaking. Maybe you just saw another pregnancy announcement and had to excuse yourself. I’ve been a fertility specialist for years, and I’ve learned something that most medical textbooks don’t teach: infertility isn’t just about biology. It’s about the silence. It’s about shame. It’s about lying awake at 3 AM wondering if something is fundamentally wrong with you. I’m writing this because I want you to know something before you even come to see me: You are not broken. You are not alone. And what you’re feeling is real—it’s valid, and it matters. The Truth Nobody Tells You Let me be honest with you from the start. One in six couples globally struggle with infertility. That’s millions of people. But infertility is still treated like a secret—whispered about in private, hidden from friends and family. Women carry this shame alone while their bodies become a source of grief instead of joy   Here’s what I see in my clinic every single day: intelligent, accomplished, beautiful women who have somehow internalized the belief that they’ve failed. That there’s something fundamentally defective about them. Men who feel emasculated and confused. Couples who used to laugh together and now can barely look each other in the eye   The emotional weight is real. Research shows that women experiencing infertility report anxiety and depression levels comparable to cancer patients. Not because infertility is life-threatening, but because it attacks something primal—your dreams, your identity, your vision of your future family   And here’s the heartbreaking part: 48% of couples avoid seeking help because they can’t face a formal diagnosis. They’d rather suffer in silence than admit something is wrong.   If that’s you—I’m asking you to pause that thinking right now. Please. What Changed When I Started Listening I remember the exact moment everything shifted in my practice. A couple came in after their third failed IVF cycle. The woman was hollow-eyed and broken. Her husband sat silently, disconnected. I started with the science, the data, and the next protocol. And she cried and said, “I don’t need to know about percentages. I need to know that you believe in us. I need to know this isn’t hopeless.” That changed me. I realized that every patient walking into my clinic wasn’t asking for complicated medical jargon. They were asking for something deeper: hope wrapped in truth, delivered with compassion. So I stopped treating infertility as purely a medical problem. I started treating couples as whole human beings experiencing a life crisis. I started listening more than I talked. And—this matters—I started explaining everything in simple language because you shouldn’t need a medical degree to understand your own treatment. Here’s What I Actually See When You Come In When you walk through my door, I don’t see you as a “case” or a “protocol.” I see a person who’s been carrying this alone. I see your courage in finally seeking help. I see someone who deserves clarity, honesty, and a plan designed specifically for you—not a generic package.   The first thing we do is listen. We will talk about your story. When did this start? How long have you been hoping? What’s the hardest part of this journey for you? What matters most to you in treatment?   Then we do the tests. These aren’t meant to shame you or label you. They’re detective work. They’re us trying to answer the question: What is actually preventing your body from doing something it’s designed to do? Once we know the answer, everything else becomes clear. The Three Pathways—And Why One Size DOESN’T Fit All Here’s where most fertility practices get it wrong: They have a protocol, and they plug you into it. IVF for everyone. Because it has the highest success rates, so obviously it’s best, right? No. That’s not medicine. That’s laziness. Real medicine means understanding your specific situation and choosing the gentlest, most effective path for you. Pathway 1: When We Start Gentle (PCOS, Hormonal Imbalance, Mild Issues) Some of you need medication. Maybe your cycles are irregular, or your hormones are out of balance. In recent years, something remarkable happened: we discovered a combination of Metformin + Myo-Inositol that actually works brilliantly for PCOS. Not expensive. Not invasive. Just smart medicine.   I had a patient, Priya, who was diagnosed with PCOS. She came to me expecting to jump straight to IVF, fearing it would cost ₹2-3 lakhs. Instead, we started her on this combination therapy for about ₹4,000 a month. After three months, her cycles regulated. After six months, she was pregnant naturally. Total cost: ₹32,000. Total time: seven months. She avoided ₹3,00,000 in IVF costs and the emotional intensity of high-tech treatments   If you’re under 35 with regular-ish cycles and clear tubes, we often start with IUI (intrauterine insemination). It’s like nature’s version, but we help it along. Success rates are 10-25% per cycle—and when you do the math across multiple cycles, many couples get pregnant this way.   The point: We escalate only when necessary, not because it’s profitable. Pathway 2: When We Need Structure (Blocked Tubes, Severe Male Factor) Some of you have structural problems we can’t work around. If both your fallopian tubes are blocked, no amount of medication will help—the egg and sperm will never meet. In that case, IVF isn’t an option. It’s the only logical choice. Similarly, if a partner’s sperm count is extremely low, or the sperm aren’t moving properly, trying IUI is like asking someone to climb a mountain without ropes. We use ICSI—a specialized IVF technique where we inject a single sperm directly into the egg. Fertilization rates go from 10% to 70-80%. That’s not up-selling. That’s using the right tool for the job.   IVF success rates for women under 35

The Real Truth About Infertility: A Letter From Dr. Sharmistha Sarkar Read More »

PGT in IVF: How Genetic Testing Can Improve Your Chances – Dr.Sharmistha

In the era of modern reproductive science, one of the most powerful advancements we have today is PGT in IVF. When you are on your IVF journey, this genetic test helps you choose the healthiest embryos for transfer.  Preimplantation Genetic Testing (PGT) is a method that is used in conjunction with IVF to select the healthiest embryos for transfer before implantation. This method helps to improve chances of pregnancy and reduce the high risk of miscarriage.  Types of PGT Testing: There are mainly three types of PGT Testing- PGT-A (Preimplantation Genetic Testing for Aneuploidy) PGT-M(Preimplantation Genetic Testing for Monogenic Disorders) PGT-SR(Preimplantation Genetic Testing for Structural Rearrangements) PGT-A (Preimplantation Genetic Testing for Aneuploidy): This is the most common type of genetic testing. It generally detects conditions where the number of chromosomes is abnormal such as Down Syndrome, where there is an extra chromosome 21, or Turner syndrome, where there is only one X chromosome present in a female’s body. PGT-M(Preimplantation Genetic Testing for Monogenic Disorders): In this genetic screening, the embryos that carry genes with any genetic disorder are detected and the healthiest embryos are selected for transfer. PGT-M is ideal for those couples who carry such conditions which can be passed on to their children. PGT-SR(Preimplantation Genetic Testing for Structural Rearrangements): Structural chromosomal abnormalities such as translocation or inventions often lead to higher chances of miscarriage or infertility. Embryos that carry these structural abnormalities are identified and the embryos that are more likely to result in a successful pregnancy are selected  by fertility specialists. Benefits of PGT in IVF: Higher success rates: Choosing chromosomally normal embryos increases the chances of successful implantation. Lower risk of miscarriage: Genetic issues are a common cause of pregnancy loss; detecting them early helps avoid heartbreak. More confident embryo selection: Instead of guessing, you get scientifically guided choices. Safer single-embryo transfer: With PGT-tested embryos, you can often transfer just one embryo with greater confidence.   Reduced risk of inherited disorders: PGT can identify specific genetic conditions that might run in a family.     PGT in IVF is especially recommended for: Women above 35 Couples with a history of recurrent pregnancy loss Parents who are carriers of known genetic conditions Couples with multiple failed IVF cycles Cases of severe male-factor infertility  If you aren’t sure whether you fall into these categories, don’t worry, personalized guidance is key, and that’s where Dr.Sharmistha’s expert consultation helps.    PGT in IVF (Preimplantation Genetic Testing) is more than just an advanced laboratory step, it’s a way to bring clarity, confidence, and hope into your fertility journey. By helping identify the healthiest embryos, PGT can improve IVF success rates, reduce the risk of miscarriage, and support safer, more informed decisions. While it may not guarantee pregnancy, it gives couples a better chance at achieving the healthy baby they dream of.   With expert guidance and the right fertility care, PGT can become a powerful part of your personalized IVF plan. If you’re considering IVF or exploring ways to enhance your chances, consult a fertility specialist like Dr. Sharmistha who can help you understand whether PGT is the right choice for you.     “Start your IVF journey with confidence Schedule your appointment with Dr. Sharmistha today!”

PGT in IVF: How Genetic Testing Can Improve Your Chances – Dr.Sharmistha Read More »