
Dr Sharmistha

Fertility Treatment

Life During and After IVF Treatment: What Patients Should Know

Beginning the IVF (In Vitro Fertilization) process is one of the most important choices couples can take in their adventure towards parenthood. While the most focus goes to the medical process itself, in reality, the patients may want to understand what happens during their everyday life in the course of treatment and also after it is over. Knowing what each phase involves can be very beneficial in terms of alleviating anxiety around the process. Understanding the IVF Journey: An Overview IVF is a multi-step process that typically spans four to six weeks per cycle. It involves ovarian stimulation, egg retrieval, fertilization in a laboratory, and embryo transfer. While the science behind IVF has advanced tremendously, every patient’s experience is unique, shaped by their medical history, age, and underlying fertility challenges.   Many patients searching for guidance turn to a trusted infertility specialist in Siliguri to better understand their treatment options and what lies ahead. Having the right medical support during this time makes a meaningful difference-not just in success rates, but in how manageable the entire experience feels. Life During IVF Treatment 1. The Stimulation Phase The process normally starts with hormone injections aimed at stimulating the ovary to release many eggs. This phase lasts for 8-14 days, during which the patient is supposed to:   Have frequent visits to the clinic to undergo blood and ultrasound tests for follicles’ measurement Experience bloating, sore breasts, or mood changes resulting from the effects of hormones Need to inject regularly in a timely manner It is crucial to communicate openly with your fertility doctors during this stage. Any symptoms, such as severe stomach pain or weight gain, should be reported immediately since they may indicate Ovarian Hyperstimulation Syndrome (OHSS). 2. Egg Retrieval and Fertilization After the eggs have attained the right size, a small surgery is conducted to collect the eggs, which only takes one or two days for the patient to recover, although there may be some cramping and light bleeding. The collected eggs are then combined with sperm in the lab through insemination or ICSI. 3. Embryo Transfer and the Two-Week Wait Three to five days after the development of the embryo, the embryos are implanted in the uterus. The following process is referred to as the infamous “two-week wait,” which is the waiting period from implantation to the pregnancy test. This period is known as the most difficult emotional stage of IVF.   Some tips for this period are: Do not engage in strenuous exercises but keep your routine activities light Take the prescribed progesterone medications regularly Use stress management strategies such as walking or meditation Do not look out for signs, since symptoms of pregnancy and side effects of medicines are alike Managing the Emotional Rollercoaster IVF is a process which can prove quite emotional. Patients tend to feel a variety of emotions such as fear, hope, disappointment, among others and all on one single day. This is very normal.   Some ways of coping include:   Creating a network of supporters. You can talk to a partner, friend or a support group which will make you feel less alone. Try counseling. More often than not, many clinics will have counselors in place for their patients to help cope with fertility related stress. Set boundaries with those people who do not seem to appreciate the emotional toll that comes with the process. Be patient with your body. Hormones will play a big role in affecting your moods and energy level. What Happens After a Positive Pregnancy Test? A positive beta hCG result means that it’s time for happiness and peace of mind, but there is much more ahead. Some steps still need to be taken during the first trimester after conception through IVF procedure:   Continuing hormonal therapy: Estrogen and progesterone therapies continue until week 8-12 of the pregnancy period. Early ultrasound scans: They detect pregnancy position (check for ectopic pregnancy) and detect the fetal heart rate at week 6-7 of pregnancy. Regular monitoring: An IVF pregnancy requires slightly more regular examinations due to the presence of preconditions like PCOS or an advanced age of patients. Once the pregnancy becomes stable and is passed from the first trimester stage, a normal OB/GYN schedule can be followed. What If the Cycle Is Unsuccessful? Not every in vitro fertilization cycle leads to pregnancy, and that is one of the most difficult facts patients have to cope with. When a cycle does not work, it should be remembered that:   One failure does not automatically mean future failures Your fertility doctor usually analyzes the cycle thoroughly and makes adjustments necessary Having more frozen embryos will give you an opportunity to conduct another cycle without conducting the whole stimulation again It is completely natural to take some time to mourn and recover before making the next step Communicating openly with your doctors about what did not work well and what should be adjusted is one of the key points of the process. Long-Term Physical Health After IVF In addition to the immediate consequences, women have concerns over what IVF means for their health in the future. According to recent scientific studies, IVF does not harm a person and causes only temporary physical consequences linked to hormonal therapy. But keeping up a healthy lifestyle – eating properly, exercising moderately, and avoiding stress – helps you stay in good reproductive and general condition, regardless of the treatment result.   It is important to have regular check-ups even when the treatment has been successful or unsuccessful. Practical Tips for Patients Undergoing IVF Maintain a treatment calendar: Log in medications, appointments, and test results to keep track. Schedule recovery periods: This is particularly important around the time of retrieval and transfer. Consult with work if necessary: Some patients choose to discuss their situation with the employer for scheduling, and others prefer not to-it depends on your personal choice. Do not hesitate to ask questions: Any and all questions are relevant in the case of your

Life During and After IVF Treatment: What Patients Should Know Read More »

Can Endometriosis Cause Infertility? Understanding the Connection

Being diagnosed with endometriosis, or perhaps even suspecting that you may have it, will bring up a number of questions in your mind, but one in particular that will definitely be prominent is whether endometriosis causes infertility. This is a legitimate worry, as there are quite a few cases where women are facing this issue and don’t get the right information or help from anyone. But the thing is that endometriosis-induced infertility is not something unknown in medical circles, and, if you consult an expert fertility doctor, you will be able to become pregnant successfully.. What is Endometriosis? Endometriosis is an illness wherein tissues like that lining the uterus are found outside the uterus – most likely growing on the ovaries, fallopian tubes, and the lining tissues of the pelvis. But unlike the uterine lining tissue that sheds itself during the menstrual period, this tissue has nowhere to go once it is shed. Hence, it causes inflammation, scarring, and adhesions (scar tissues that make the organs bind to each other).   There are millions of sufferers of endometriosis all around the world, but many of them remain undiagnosed for several years as the symptoms are usually dismissed as just menstrual pains. Common Symptoms of Endometriosis Periods (dysmenorrhea) that cause severe pain that increases with time Sexual pain Pelvic pain that is not limited to periods Severe period bleeding or bleeding outside of periods Digestion problems like bloating, constipation, or diarrhea, particularly during your periods Fatigue Difficulty becoming pregnant These are some of the signs and symptoms that indicate you may need to see an infertility specialist. So, Can Endometriosis Cause Infertility? Absolutely, because endometriosis is one of the main reasons for women’s infertility. The researches show that there is a certain percentage of women who have trouble with conception, ranging from 30 to 50%. But it should be taken into account that not all women suffering from endometriosis will face the problem of infertility, because it does not necessarily depend on the severity of endometriosis. Let’s see how endometriosis can prevent conception. 1. Distorted Pelvic Anatomy With the growth of endometrium-like tissue and formation of scar tissue, the ovaries, fallopian tubes, and uterus may get displaced. This displacement of organs will make it hard for the egg cell to move from the ovary to the fallopian tube, thus preventing fertilization. 2. Blocked or Damaged Fallopian Tubes In the most severe case, endometriosis will lead to the development of adhesions which will block the fallopian tubes completely, thus preventing the sperm cell from getting to the egg or vice versa. 3. Inflammation Affecting Egg and Sperm Quality Endometriosis can cause chronic inflammation in the pelvic cavity. This inflammation might affect not only the egg and sperm cells but also the embryo itself. 4. Ovarian Reserve Reduction Chocolate cysts, which are also known as endometriomas, are one form of ovarian cysts related to endometriosis. Endometrioma can destroy normal ovarian tissue and decrease the woman’s ovarian reserve, meaning the amount of good quality eggs that can be used in conception. 5. Implantation Issues Although fertilization might happen, endometriosis can make the uterus not receptive enough for the implantation of the embryo. Diagnosing Endometriosis-Related Infertility In case you have been struggling with conception problems and think that you may have endometriosis, meeting an expert in infertility would be your initial move. The diagnostic procedure usually includes:   Detailed medical history and symptom review Pelvic examination Ultrasound imaging to detect cysts or abnormalities Laparoscopy, considered the gold standard for confirming endometriosis, which allows direct visualization and, in many cases, treatment during the same procedure Dr. Sharmistha Sarkar emphasizes the importance of early diagnosis, as timely intervention can significantly improve fertility outcomes for women with endometriosis. Treatment Options for Endometriosis and Infertility The correct treatment depends on the severity of the disorder, the woman’s age, and the duration of her efforts to get pregnant. The following treatment modalities are commonly used: Medication Treatment It helps to control pain and to slow down the progression of endometriosis; however, hormonal therapy is usually avoided while a woman is trying to conceive because most medications affect the ovulation process. Laparoscopy This minimally invasive procedure allows for the removal of endometrial tissue, cysts, and adhesions and increases fertility, especially if endometriosis is mild to moderate. Ovulation Induction Fertility drugs and controlled ovulation may assist in getting pregnant naturally in the case of mild endometriosis. Intrauterine Insemination (IUI) In some cases, intrauterine insemination is indicated along with ovulation induction. In Vitro Fertilization (IVF) If a woman has endometriosis to the extent that she has problems conceiving by other methods, In Vitro Fertilization (IVF) will be the most appropriate method for her. In vitro fertilization will avoid many of the issues that the condition causes in conception.   An experienced fertility specialist will design a personalized treatment program for each woman. Living with Endometriosis While Trying to Conceive However, having endometriosis does not automatically exclude a woman from pregnancy. There are many cases where women with this disease have successfully conceived both naturally and artificially. Here are some pieces of advice that might come in handy when attempting to conceive with endometriosis:   Do not waste time. Seek professional help immediately if you cannot conceive for six months to a year (or even before, if you are older than 35 years). Monitor your symptoms. Your doctor will need to know your experience of pain and the menstrual cycle in order to make the right diagnosis. Try every possible treatment. Whether it is lifestyle adjustment or complex assisted reproductive technologies, there are numerous ways to get pregnant. Look for psychological support. Dealing with fertility problems may be psychologically stressful, and discussing your issues with people who can listen is very important. Why Choose Dr. Sharmistha Sarkar Tackling infertility associated with endometriosis demands a sensitive, experienced, and meticulous method. Being an infertility specialist with extensive experience in dealing with women experiencing fertility problems, Dr. Sharmistha Sarkar is well equipped to provide personalized treatment

Can Endometriosis Cause Infertility? Understanding the Connection Read More »

Fertility After 35: Challenges and Treatment Options

Numerous women enter a consultation room and tell their doctor some variation of, “I thought I had more time.” Typically, she is 36, maybe 38, or sometimes 41 – and has realized that having children at her age is not quite as easy as she had hoped.   This confusion is no mystery. The advice that women have received for many years is nebulous, telling women only that “fertility decreases with age.” It does not explain why or what the alternatives are after 35. So let’s discuss it. What Actually Changes After 35 Women are born with all the eggs they’ll ever have – roughly one to two million at birth, down to about 300,000 by puberty. From there, the number keeps dropping every single month, whether or not someone is trying to conceive. By the mid-30s, both the quantity and the quality of the remaining eggs have declined noticeably. This isn’t a guess or a scare tactic; it’s basic reproductive biology, and it’s the reason fertility specialists talk about 35 as a turning point rather than a magic cutoff.   Egg quality matters just as much as quantity. As eggs age, they become more prone to chromosomal abnormalities, which is part of why miscarriage rates climb after 35 and why conditions like Down syndrome become more common in pregnancies conceived at older maternal ages. None of this means pregnancy after 35 is unlikely – it isn’t – but the odds do shift, month by month, in a way they don’t in the late 20s.   There’s also the practical reality that fertility issues aren’t always about eggs alone. Conditions like fibroids, endometriosis, and hormonal imbalances become more common with age too, and they can complicate conception independently of egg quality. Why this Catches so Many Women off Guard So many women were doing everything “right” according to the advice that was given to them – they were focusing on their careers, saving enough money, and finding the right person. All of these things are not wrong. However, the problem with information about fertility timelines is that it is not delivered to women in an honest way, and by the time they start thinking about having children, they have lost years they didn’t realize could be so important.   This is not intended to make women feel guilty, as guilt doesn’t contribute to conception. Instead, this is to help people understand that knowing the biology of the process helps people approach treatment differently. When to See a Specialist It is generally advised that younger women under the age of 35 seek the expertise of a fertility specialist if conception does not occur within 12 months of trying. For women over the age of 35, the window is narrowed to six months. Women over the age of 40 are urged not to wait until then, and an initial consultation once ready for conception can serve to set the benchmark while there is still more time to work with.   These are indications that warrant early consultation, irrespective of age. Testing: What Actually Gets Checked Before jumping to treatment, real information is needed. For women, that typically includes an ovarian reserve assessment – usually AMH (anti-Müllerian hormone) bloodwork paired with an antral follicle count on ultrasound – along with hormone panels and imaging to check the uterus and fallopian tubes. For male partners, a semen analysis is standard, since roughly a third of fertility issues involve male factors and it’s often overlooked early on.   Testing isn’t about assigning blame. It’s about building an accurate map so treatment decisions aren’t a guessing game. Treatment Options After 35 There is no one-size-fits-all treatment plan. It all boils down to the results of your tests, the diagnosis, and what you personally feel comfortable with. Here is a practical example of what usually comes into the equation. Changes to your lifestyle are the very first step taken, not because they cure everything, but because they eliminate certain barriers that are in your hands to control. Losing extra pounds, stress management, less alcohol and cigarettes, treatment for thyroid disorders – all this can make a real difference, sometimes even sufficient in itself. Of course, this will not help you increase the egg reserve, but it is worth starting with. Ovulation induction and IUI (intrauterine insemination) are usually the first medical steps when the fallopian tubes are open and the partner’s sperm count is normal. Medication stimulates egg release, and sperm is placed directly into the uterus around ovulation. It’s less invasive and less expensive than IVF, though success rates drop more steeply with age than they do for younger patients, so this route isn’t usually recommended indefinitely if it isn’t working. In vitro fertilization (IVF) emerges as the more straightforward method for many women who are above 35 years of age, especially those whose ovarian reserve is depleted or if other techniques have not proved effective. Eggs are collected, fertilized in the laboratory, and then one or more embryos are implanted back into the womb. The chances of success for IVF fall with age, but are considerably better compared to those of natural conception at the same age, and that is precisely why it comes up early in the discussion. Preimplantation genetic testing (PGT) is an option that could be incorporated into an IVF treatment cycle to detect chromosomal abnormalities in embryos before their transfer. Although this technique does not enhance the quality of eggs, it may decrease the risk of miscarriage as the embryo which is most viable is selected. Donor eggs become a genuine, and often successful, option when a woman’s own egg reserve or quality has declined significantly. It isn’t the first choice most people imagine for themselves, and it deserves an honest conversation rather than being avoided. For many patients, donor egg IVF offers by far the highest success rates of any option available after 40. Egg freezing, ideally done earlier, is worth mentioning too, since women in their late 30s often

Fertility After 35: Challenges and Treatment Options Read More »

How Obesity Affects Fertility in Women: Everything You Need to Know

You’re eating right, mostly. You’re tracking your cycle down to the day. You’ve read every article the internet has to offer. And still, month after month, nothing.   Sound familiar? Then there’s probably a piece of this puzzle nobody’s mentioned to you yet – not at the dinner table, and sometimes not even in the doctor’s office. Weight. Obesity and fertility in women are far more connected than most people ever get told, and once you see the link, a lot of confusing symptoms suddenly click into place.   Let’s get one thing straight first. This isn’t about blame. It’s not about shame. It’s just biology, doing what biology always does. Fat tissue isn’t some passive layer just sitting there minding its own business. It’s actually working overtime – pumping out hormones, messing with your insulin, constantly chatting with your reproductive system whether you notice it or not. And when that conversation gets a little too loud, fertility is usually the one that pays for it. The Basic Connection Nobody Explains Well Think of fat tissue less like storage and more like an active organ. It produces estrogen. It releases leptin. It sends out inflammatory signals. In normal amounts, this is fine -even necessary. But when body fat climbs significantly, so does this hormone output, and things get noisy.   That extra noise interferes with the very precise signals your brain sends to your ovaries every month. Instead of a clean, predictable cycle, you start seeing delays, skipped periods, or cycles that never quite build up to ovulation at all.   This is really the heart of obesity and fertility in women -it’s not about a number on a scale. It’s about what that number is quietly doing to your internal hormone environment. How Ovulation Gets Thrown Off Track Ovulation is basically a hormone relay race. Estrogen, progesterone, LH, FSH -they all need to hand off to each other at exactly the right moment for an egg to mature and release.   Extra fat tissue produces additional estrogen on top of what your ovaries are already making. Your brain sees this and essentially thinks, “hormones are already high enough, no need to trigger ovulation.” So it doesn’t. Cycles get longer. Some months, ovulation doesn’t happen at all.   If you’ve noticed your periods getting unpredictable, this is often the first visible sign of obesity and female fertility issues -long before anyone starts actively trying to conceive. The Insulin Piece Most People Miss Here’s something that rarely comes up in casual conversation: obesity is closely tied to insulin resistance. Your cells stop responding to insulin the way they should, so your pancreas compensates by pumping out more of it.   That excess insulin pushes your ovaries to produce more androgens -yes, the same hormones associated with male characteristics. This throws off follicle development and, again, disrupts ovulation.   This is also a big reason obesity and PCOS show up together so often. And PCOS, on its own, is one of the most common causes of infertility today. The good news is that managing insulin -through food choices, movement, sometimes medication -tends to improve ovulation fairly reliably. Why Your Doctor Keeps Bringing Up BMI If your doctor keeps circling back to your BMI during fertility conversations, it’s not a throwaway comment. There’s real research behind it. BMI and fertility outcomes are linked pretty consistently across studies.   Higher BMI tends to show up alongside: A longer stretch of time trying to conceive naturally Lower success rates with treatments like IUI and IVF A higher chance of miscarriage after conception More pregnancy complications down the line None of this means a higher BMI equals infertility -plenty of women with higher BMI conceive naturally and have completely healthy pregnancies. But statistically, the odds shift a bit, and it’s better to know that early than to find out the hard way. It Doesn’t Stop at the Positive Pregnancy Test Something that gets overlooked constantly: overweight and fertility struggles don’t end the moment you conceive. They can follow you right through the pregnancy.   Higher body weight during pregnancy is linked to a higher chance of gestational diabetes, high blood pressure, needing a C-section, and complications during delivery. So the real question isn’t just “can I get pregnant.” It’s also “how smoothly will this pregnancy go once I am?” Does Weight Actually Affect Fertility Treatment Success? It does, and this surprises a lot of people. Women with higher BMI often see somewhat lower success rates with IVF and IUI. Part of this comes down to egg quality. Part of it comes down to how the body responds to fertility medications -sometimes needing higher doses to get the same effect. And part of it involves the uterine lining and how well an embryo can implant.   Because of this, a lot of fertility clinics now build weight management directly into the treatment plan instead of treating it as a side note. A fertility specialist will often suggest addressing weight before diving into treatment cycles, simply because it tends to improve the odds. Here’s the Genuinely Good News This isn’t a life sentence. Research shows that losing even five to ten percent of body weight can meaningfully improve ovulation and rebalance hormones for a lot of women. That’s a realistic target -not a total life overhaul.   Plenty of women see their cycles regulated again within a few months of steady, sustainable changes. This is exactly why doctors push back against crash diets and extreme restrictions. Those approaches often backfire, adding stress to the body that makes hormonal imbalances worse, not better. What Actually Helps You don’t need to overhaul everything overnight. Small, consistent habits tend to move the needle more than dramatic short-term changes.   Eating balanced meals with enough protein, fiber, and healthy fats -instead of chasing the latest restrictive diet trend -matters more than most people expect. So does simply moving your body regularly; something as basic as a daily walk can improve insulin sensitivity

How Obesity Affects Fertility in Women: Everything You Need to Know Read More »

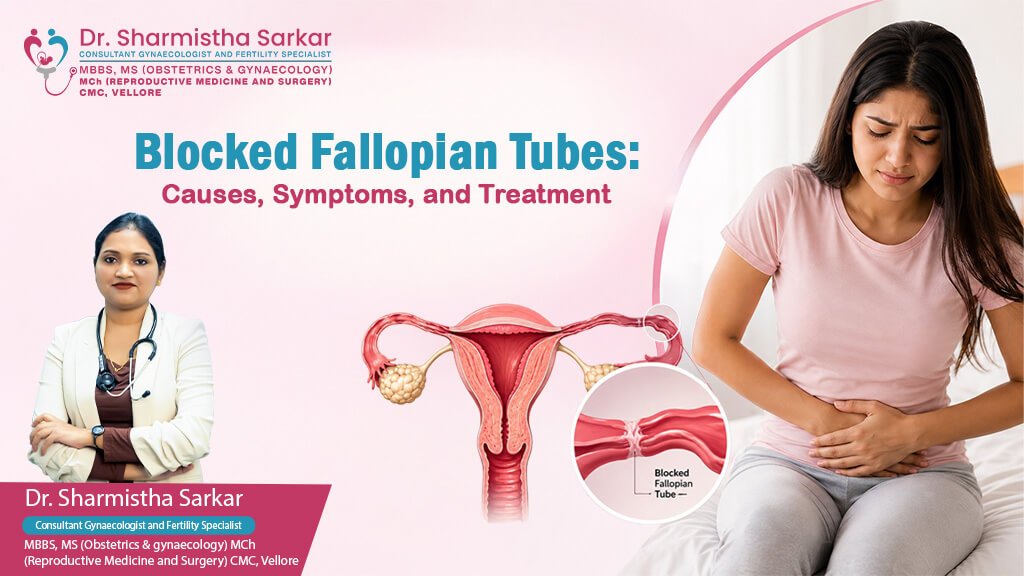
Blocked Fallopian Tubes: Causes, Symptoms, and Treatment

If you’ve been attempting to conceive without any success, you might have to seek out help. You’re not alone. No one knows why, and many women suffer from this silently. Hope is constantly replaced by frustration, every month. Test results are normal, but the pregnancy does not occur. Frequently, blocked fallopian tubes are overlooked.   There are relatively few symptoms of this condition. However, it is a significant factor in fertility problems in the world.   It is believed to be one of the main contributors to 20% of the cases of unexplained infertility in clinics today.   Let’s take this apart. Simply. Clearly. Without the jargon used by doctors. What Are Fallopian Tubes and How Do They Work? Consider these like miniature highways. Fallopian Tubes are tubes that link your ovary to your uterus.   This tube is used to transport an egg each month. Sperm and egg form a zygote, or fertilized egg, here. Now, just suppose that the highway is blocked.   The egg is unable to move. Sperm will not be able to make it there. As long as they cannot get them to breed.   So what is a tubal blockage? And it is more prevalent than most women think.   The blockage could occur anywhere on the tube. Near the ovary. In the middle. Or just at the point where it is attached to the uterus. The place is important as it will influence diagnosis and treatment options later. Why Fallopian Tube Health Matters for Fertility There are numerous factors that influence fertility.   Hormones. Ovulation. Uterine health. And importantly, open, functional tubes. If there’s a blockage in the fallopian tube, even if the hormones are perfect, pregnancy may be impossible.   That’s why doctors always examine tube health when evaluating fertility. It’s a part of a puzzle that’s simple to overlook, but hard to overlook.   A large proportion of the female infertility cases that are encountered in the clinics today are due to blocked fallopian tubes. Common Symptoms of Fallopian Tubes Here’s the tricky part. Most women do not experience anything abnormal.   That’s right. Blocked fallopian tube symptoms can be vague, sometimes not present at all, which is why women may not find out they have a blocked fallopian tube until they are undergoing fertility testing.   However, some symptoms might occur such as: Slight to medium pain in the pelvis area. Unusual vaginal discharge Periods that are painful, worse than usual Pain during intercourse The doctor will ask you about any previous infections you’ve had in the pelvis. If you see these signs and complain of trouble getting pregnant, it’s advisable to get checked. Prevention is better than cure.   Take care – no symptoms, no problems! That’s why fertility testing is important – it can detect what the average person can’t. What Causes for Blocked Fallopian Tubes? The knowledge of the cause assists in providing appropriate treatment.   These are the most usual causes of blocked Fallopian tubes:   Pelvic Inflammatory Disease (PID) – May be due to untreated sexually transmitted infections such as chlamydia or gonorrhea. This is one of the main causes of damage to the tubes.   Endometriosis – Growth outside of the womb may be able to entangle or scar the tubes.   Previous surgeries – Surgery to the abdomen or pelvis may cause scar tissue to develop and obstruct the tubes.   Ectopic pregnancy history – Scars and damage to the affected tube can occur after an ectopic pregnancy.   Fibroids – If there is a large fibroid near the tubes, sometimes it can put pressure on the tubes and block them.   Untreated infections – If left untreated for too long, the risk of an infection of the pelvis is greatly increased.   Tuberculosis – Genital tuberculosis is an unrecognized but actual cause of tubal scarring in some areas.   If your doctor knows your past history, he or she can quickly identify the likely cause. How Are Blocked Fallopian Tubes Diagnosed? There are a few key tests that are typically used to diagnose.   Hysterosalpingography (HSG) – A special dye is inserted into the cervix. After this, X-rays will be taken to determine if the dye can flow freely through the tubes. This procedure is still the most frequently used to diagnose fallopian tube blockage.   Laparoscopy – A minor surgical procedure using a small camera. This enables them to see blockages and other pelvic problems directly.   Sonohysterography – A test that uses ultrasound, which is sometimes used as the first screening test.   None of these tests are intended to frighten you. They just provide your doctor with a map of what’s going on inside, and guesswork is replaced by facts. The correct test will be suggested according to your medical history and symptoms. Blocked Fallopian Tubes and Infertility: What’s the Connection? Let’s address this directly.   Blocked tubes and infertility are closely linked, but a blockage doesn’t always mean pregnancy is impossible.   If only one tube is blocked, natural conception may still happen through the healthy tube.   If both tubes are blocked, natural conception becomes very difficult. But medical treatments still offer real hope.   This is why proper diagnosis matters so much. It tells you exactly what you’re working with, not just guessing based on symptoms alone. Blocked Fallopian Tubes Treatment: Options That Work Next, the part you’ve all been waiting for.   If you have blocked fallopian tubes treatment will vary depending on the location and severity of the blockage.   Tubal surgery – Sometimes, surgeons will be able to remove scar tissue and open the tube. The extent of the damage is the determining factor for success.   Laparoscopic surgery – A simple procedure that may be used for mild blockages or to remove scar tissue.   In Vitro Fertilisation (IVF) – IVF is used when tubes are so damaged or surgery unsuccessful. The egg and sperm fuse in the ‘outside’, and the

Blocked Fallopian Tubes: Causes, Symptoms, and Treatment Read More »

How Thyroid Disorders Can Affect Your Fertility and Chances of Conception

You’ve been trying for months. Maybe years. Same hope every cycle. Same heartbreak every month.   You eat well. You track ovulation. You take vitamins. You do everything right. Yet nothing happens.   Here’s a secret most people miss. The answer might not be in your ovaries. It might be in your neck.   A tiny gland called the thyroid could be the missing piece. It’s small. It’s quiet. But it controls more than you think. The link between thyroid disorders and fertility is real, and it’s stronger than most women realize.   Think of your body like an orchestra. Every organ plays a part. When one instrument goes out of tune, the whole song changes. The thyroid is that instrument. When it’s off, your cycle feels it. Your ovulation feels it. Your chances of conceiving feel it too.   Let’s break this down, simply and clearly. What Does the Thyroid Actually Do? The thyroid is a small, butterfly-shaped gland at the base of your neck. Don’t let its size fool you – it controls far more than most people realise.   This is a gland that regulates your metabolism. It controls your energy. It impacts your heart rate and body temperature. It is also a very important factor in reproductive health.   If thyroid levels are elevated or depressed, your entire body chemistry changes. One of the first places this is evident is in your menstrual cycle. The Real Connection: Thyroid Disorders and Fertility Let’s get on with it. Thyroid and fertility go hand in hand.   Hormone balance is essential to healthy cycling. Estrogen and progesterone must have the proper rises and falls. Ovulation must occur in a timely fashion. If not, it does not work out.   This balance is disturbed when the thyroid fails. Periods become irregular. Ovulation becomes unpredictable. Without regular ovulation, pregnancy becomes difficult.   This is the principal problem that leads to thyroid problems and fertility issues. Easy but forgotten. Hypothyroidism and Fertility: An Underactive Thyroid One major cause is an underactive thyroid. This is called hypothyroidism .   Hypothyroidism and fertility issues go hand in hand more often than people realize. An underactive thyroid slows everything down. Energy drops. Metabolism slows. Hormone signals get confused.   This confusion disrupts ovulation. No ovulation means no egg release. No egg release means no chance of natural conception that month.   Many women live with hypothyroidism and fertility struggles without knowing why. They blame stress. They blame age. They blame timing. The real answer is often a simple blood test away. Hyperthyroidism: The Other Side of the Coin An overactive thyroid causes problems too. This condition is called hyperthyroidism.   It speeds up your body’s systems. Heart rate increases. Cycles shorten or become irregular. Ovulation gets disrupted again, just from the opposite direction.   Whether the thyroid works too slow or too fast, the result is similar. Thyroid disorders and fertility challenges appear either way. Thyroid Disorders and Conception: Why It Matters So Much Conception isn’t just about releasing an egg. It’s about creating the right environment for a pregnancy to begin and grow.   Thyroid disorders and conception are linked at every stage. A healthy thyroid supports a strong uterine lining. It helps maintain good egg quality. It supports early pregnancy hormone levels too.   Even a slight imbalance in thyroid can alter the process. That’s why doctors often suggest a thyroid test as a first step for couples facing conception delays. Signs Your Thyroid Might Be the Problem These symptoms are easy to overlook. But they matter.   Irregular or missed periods Sudden weight gain or weight loss Constant fatigue Thinning hair Mood swings or anxiety Trouble conceiving despite trying If several of these sound familiar, don’t ignore them. They could be quietly pointing to thyroid disorders and fertility issues. You should contact Dr Sharmistha Sarkar for evaluation and diagnosis. Why So Many Women Miss This Thyroid symptoms are well hidden. They become a part of everyday life.   Tired? Must be work stress. Irregular periods? Probably just hormones. Mood swings? Just a bad week.   But when the same signs return, cycle after cycle, it’s rarely a coincidence. Women face thyroid disorders far more than men. Reproductive years are prime time for it. So many women trying to conceive carry an undiagnosed thyroid issue. They have no idea it’s there. This overlooked connection is exactly why thyroid disorders should be investigated early in any fertility journey. The Good News: It’s Treatable Here’s the good news – thyroid-related fertility issues are among the most treatable causes of conception difficulty. Most women resume normal thyroid function when they are properly diagnosed. After hormone levels settle, ovulation will resume a regular pattern. The likelihood of a spontaneous conception is greatly improved. Treatment usually includes: Thyroid hormone medication Regular blood testing Lifestyle and dietary changes Close supervision of the entire pregnancy planning process. The sooner the diagnosis is made, the smoother the journey. The stress that comes with waiting just increases the emotional impact of an already emotional process. Why You Need a Specialist, Not Guesswork When it comes to thyroid and fertility, self-diagnosis is not an option.   There are accurate blood tests that can be performed by a specialist. They can determine the exact imbalance. They can create a treatment plan that is tailored to you.   This isn’t a bunch of general information. It’s about finding true answers to your thyroid and fertility issues, and they are personal to you.   Many women conceive naturally and with the proper guidance. Others use the diagnosis to better prepare for fertility treatments. In either case, knowledge is power.   Frequently Asked Questions (FAQs) Q1: Can thyroid problems really cause infertility? Yes. Both an underactive and overactive thyroid can disrupt ovulation and lower fertility. Q2: Is treating hypothyroidism and fertility issues safe during pregnancy planning? Yes. With medical supervision, thyroid medication is safe and often essential for a healthy pregnancy. Q3: How do I know if

How Thyroid Disorders Can Affect Your Fertility and Chances of Conception Read More »